
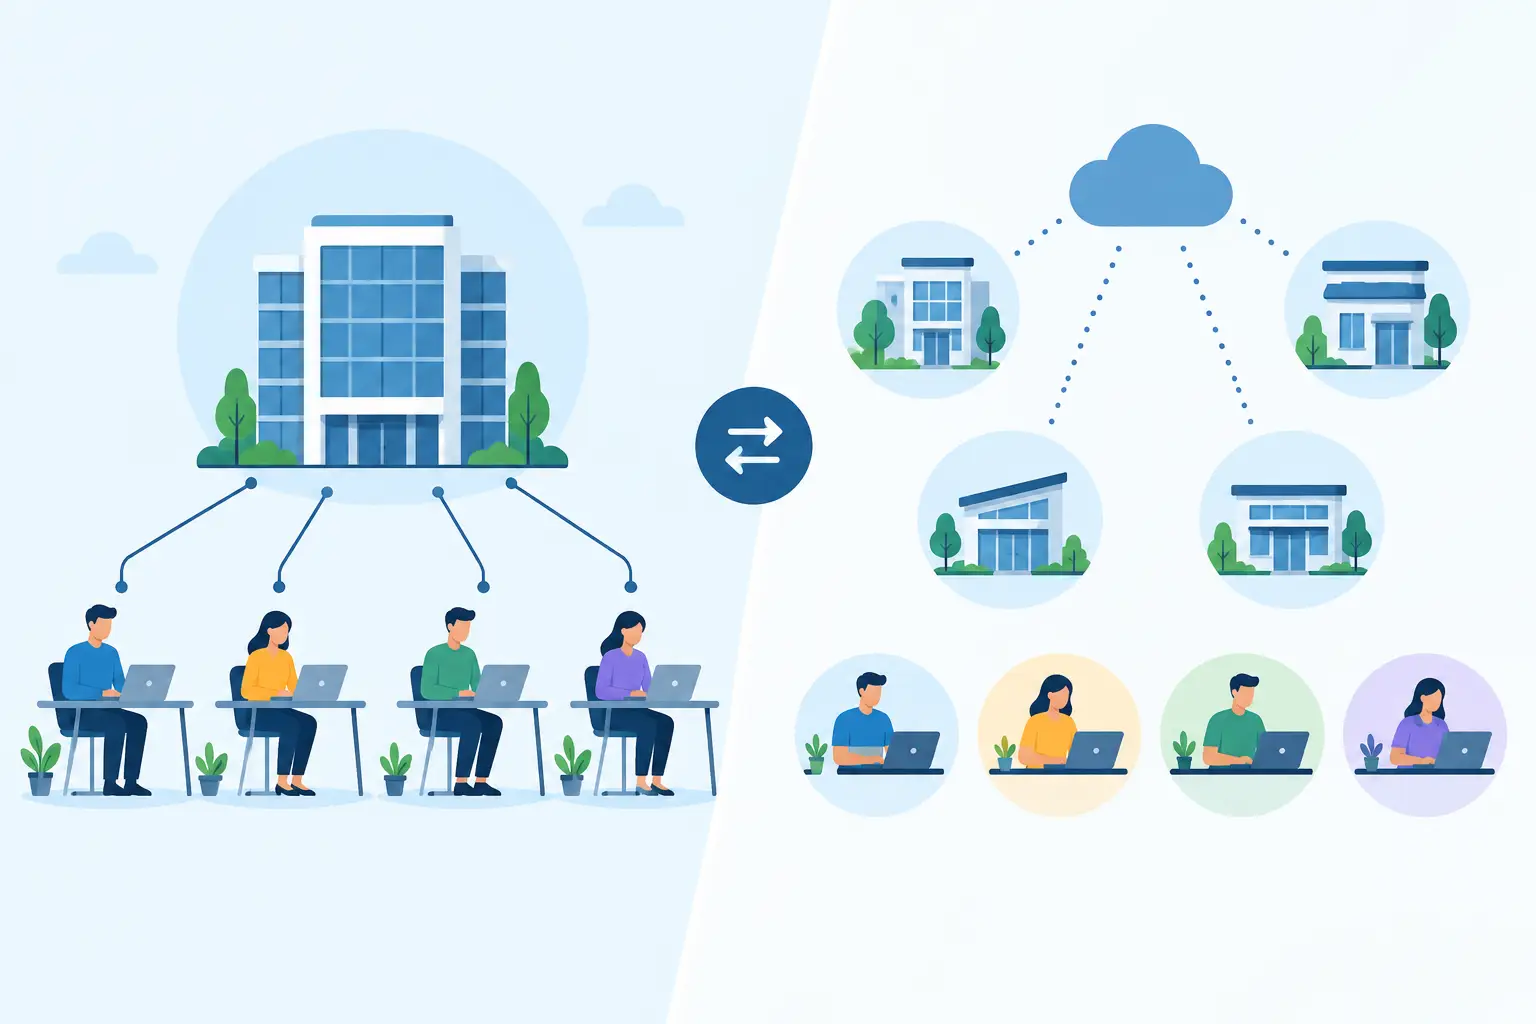
A multi-site clinic can lose control long before it notices a problem. A duplicate patient record, an uncollected invoice, an inconsistent cancellation policy or an unfilled practitioner diary may appear local, but the financial and patient-care impact is felt across the organisation. The choice between centralised versus branch administration determines how reliably a healthcare business can scale its operations.
Why centralised versus branch administration matters
Administration is not simply a question of where tasks are completed. It determines who owns the data, who can change rules, how quickly leaders can identify performance issues and whether patients receive a consistent experience at every location.
For a single clinic, local decision-making can feel quick and practical. As locations, practitioners and service lines increase, separate processes often create separate versions of the truth. Reception teams may use different booking rules. Managers may track revenue in different spreadsheets. One branch may chase overdue balances promptly while another leaves follow-up to individual practitioners.
Centralisation gives leadership a single operational framework. Branch administration gives local teams room to respond to the realities of their site. Neither model is automatically right. The effective model depends on the organisation's size, services, governance requirements and management capacity.
What centralised administration looks like in practice
Centralised administration places core rules, data and oversight under a central team or shared operating model. Branch staff may still manage daily activity, but the organisation sets the processes that govern it.
In a healthcare setting, this commonly includes one patient database, standard appointment types, system-wide cancellation rules, centrally managed practitioner accounts, common communications and unified reporting. Billing workflows, payment terms and invoice follow-up can also be controlled from one place rather than recreated at each clinic.
Consistent scheduling and patient communications
Scheduling is often the first area where fragmentation becomes visible. If each site sets its own appointment durations, availability rules and reminder messages, patients may receive materially different service depending on location. It also becomes difficult to compare utilisation, no-show rates or practitioner capacity fairly.
A central model allows operations teams to configure standard booking pathways while retaining sensible exceptions. For example, a physiotherapy group can apply common new-patient and follow-up appointment rules across its clinics, then allow a local manager to adjust availability for a practitioner who works only on certain days.
Centralised patient communications support the same objective. Shared templates, consent-aware messaging and automated reminders reduce manual work while helping every branch maintain the organisation's service standard.
Financial visibility without manual consolidation
Financial control is another strong case for centralisation. When branches use separate invoicing processes or reconcile payments outside the core system, finance teams spend time assembling data rather than acting on it.
A central billing structure can standardise fee schedules, payment collection, refunds, outstanding balances and practitioner reporting. Leaders can see which locations are collecting revenue efficiently, where debt is rising and whether changes in appointment volume are producing the expected financial result.
This does not mean every branch must be treated identically. Different sites may have different service mixes, local agreements or practitioner arrangements. The value comes from applying those variations through controlled configuration rather than disconnected processes.
Where branch administration adds value
Branch administration gives local managers the authority to make operational decisions without waiting for a central office. This can be useful where sites serve distinct populations, run different clinical services or have materially different staffing patterns.
A wellness studio with group classes may need different booking and capacity rules from a counselling practice. A city-centre clinic may need a different approach to late cancellations than a rural location where patients travel further. Local managers are often best placed to recognise these practical differences.
Local control can also improve responsiveness. A branch team that can fill cancellations, coordinate practitioner cover and resolve patient queries quickly will protect both patient experience and diary utilisation. The risk arises when local autonomy extends to changing policies, financial rules or patient data practices without visibility or approval.
The issue is not whether branch teams should have responsibility. They should. The question is whether they have responsibility within defined controls or are left to build their own administrative systems.
The risks at each end of the model
A fully centralised approach can become slow if every minor decision requires approval from head office. Branch teams may feel unable to solve immediate problems, and central administrators may make decisions without enough local context. Standardisation without flexibility can lead staff to create workarounds outside the system.
A heavily decentralised approach creates a different problem: inconsistency becomes expensive. Training takes longer, reporting becomes less reliable and patient information may be handled differently across locations. Growth then adds administration rather than producing operational leverage.
The practical aim is not maximum central control. It is controlled consistency. Centralise the areas where variation creates financial, compliance or patient-service risk, and allow branches to manage the areas where local knowledge improves delivery.
Build a hybrid operating model for healthcare
Most growing healthcare organisations need a hybrid model. Core governance remains central, while day-to-day delivery stays close to the patient and practitioner.
Central teams should normally own system configuration, access permissions, data standards, reporting definitions, billing policy, communication templates and organisation-wide booking rules. These are the controls that protect data quality, revenue visibility and service consistency.
Branch managers should normally own diary management, local staff coordination, same-day patient queries, approved schedule adjustments and follow-up on local operational issues. They need enough authority to keep the clinic running without bypassing the system.
The boundary must be explicit. If a branch needs a new appointment type, a different cancellation policy or a revised fee structure, define who can request it, who approves it and how it is recorded. If a central team changes a process, define how branches are trained and how adoption is monitored.
A good operating model also distinguishes between access and accountability. A receptionist may need permission to reschedule an appointment but not to amend a fee schedule. A branch manager may need to view local performance but not patient records from every location. Role-based permissions and audit trails support appropriate access without creating unnecessary administrative barriers.
Use reporting to test whether the model is working
The right structure should improve measurable performance, not simply make the organisation chart look tidier. Review whether clinics are following common processes and whether those processes are producing better results.
Monitor booking conversion, practitioner utilisation, cancellations, no-shows, outstanding invoices, payment collection and patient communication activity by site. Compare branch performance, but investigate context before judging a location. A clinic with more complex care pathways will not operate in exactly the same way as a high-volume treatment centre.
Look for trends that signal a control problem. Repeated manual changes, inconsistent invoice values, duplicate records and missing data usually indicate that either the central process is unclear or the local team lacks the tools and authority to complete its work properly.
Make the platform support the structure
The administration model is only as reliable as the systems behind it. Separate calendars, spreadsheets and billing tools make it difficult to centralise governance while preserving branch speed. Staff end up reconciling information manually, and leaders receive reports after the opportunity to act has passed.
A multi-clinic practice management platform should provide central configuration alongside location-level operational control. Wellspring Scheduling brings scheduling, online booking, patient management, billing, communications and reporting into one environment, giving organisations a clearer basis for standardisation without removing the flexibility branches need to manage their daily workload.
The most useful technology does not force every clinic into an identical routine. It gives leaders control over the rules that matter, gives staff a clear process to follow and makes performance visible before small local issues become organisation-wide problems.
As your healthcare organisation grows, treat administration as an operating decision rather than a background task. Clear central controls, practical branch ownership and reliable shared data give teams more time to focus on the work patients actually notice.